FRCR Part 2A · Genitourinary · Renal masses
Renal Masses: High-Yield Concepts for FRCR Part 2A
Published by FRCR AI · AI-assisted educational content
Created and overseen by Dr. Tan Min On, Radiologist — MedNex Pte. Ltd.
Published · Updated
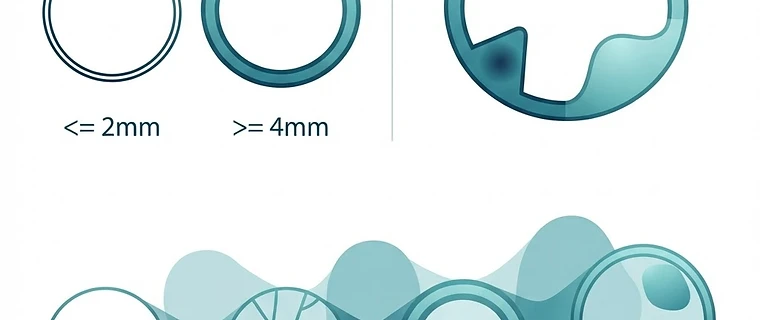
High-Yield Concepts in Renal Mass Imaging
Mastering the contemporary approach to renal masses is essential for the FRCR Part 2A exam, requiring a strict shift away from deprecated terminologies toward the precise definitions provided by the WHO Classification of Paediatric and Adult Renal Tumours (5th Edition, 2022) and the Bosniak 2019 criteria.
1. The Bosniak 2019 Update
The 2019 revision emphasizes objective metrics, explicitly limiting the system to cystic masses with less than 25% enhancing solid components. It specifically excludes necrotic solid masses from this classification. Key threshold definitions include:
- Thin wall/septa: ≤ 2 mm
- Thick wall/septa: ≥ 4 mm (Bosniak III)
- Irregularity: ≤ 3 mm protrusion with obtuse margins (Bosniak III)
- Nodule: Enhancing convex protrusion with acute margins (any size) or ≥ 4 mm with obtuse margins (Bosniak IV).
Importantly, isolated thick, nodular, or extensive calcifications are now downgraded and categorized as Bosniak II (previously IIF), as calcification alone does not independently predict malignancy. Exam Tip: Memorize the 2 mm/4 mm thresholds and the morphological distinction between irregularities and nodules based on their angles.
2. WHO 2022 Updates and Retired Terminology
Following the WHO 2022 guidelines, the subdivision of papillary RCC into Type 1 and Type 2 is retired, as Type 2 represents a heterogeneous collection of tumors rather than a distinct biological entity. Furthermore, the term "multilocular cystic renal cell carcinoma" is officially deprecated; the correct entity is "Multilocular Cystic Renal Neoplasm of Low Malignant Potential" (MCRNLMP), reflecting its indolent, non-metastatic behavior. Exam Tip: If a question presents "Type 1 or 2 Papillary RCC," recognize this as outdated terminology. Similarly, be vigilant for the transition of "Clear Cell Papillary Renal Cell Carcinoma" to "Clear Cell Papillary Renal Cell Tumor" to align with its indolent nature.
3. Clear Cell RCC vs. Lipid-Poor AML
Both tumors demonstrate microscopic (intracellular) fat resulting in signal drop on out-of-phase chemical shift MRI. Differentiation relies on signal characteristics and contrast kinetics:
- Clear Cell RCC: Characteristically T2 hyperintense with avid, heterogeneous arterial phase enhancement.
- Lipid-poor AML: Typically T2 hypointense and demonstrates more homogeneous, persistent enhancement.
Exam Tip: T2 hypointensity is a high-yield 'negative' predictor for Clear Cell RCC, making lipid-poor AML a more likely diagnosis in an equivocal, lipid-poor lesion.
4. TNM Staging and T3a Nuance
The AJCC 8th edition staging defines T3a as tumor extension into the renal vein or its segmental branches, invasion of the pelvicalyceal system, or perinephric/renal sinus fat. A critical distinction is that renal sinus fat invasion is considered a higher-risk prognostic factor compared to peripheral perinephric fat invasion. Examiners test the differentiation between T3a (local extension) and T3b/T3c (IVC involvement).
| Feature | Clear Cell RCC | Lipid-Poor AML |
|---|---|---|
| T2 Signal | Hyperintense | Hypointense |
| Enhancement | Avid, Heterogeneous | Homogeneous |
| Chemical Shift | Drop (Microscopic) | Drop (Microscopic) |
Key Takeaway: Success in the FRCR Part 2A requires current terminology (e.g., MCRNLMP, Bosniak 2019) and the ability to differentiate common renal mimics. Prioritize the 25% solid component rule for Bosniak classification and the T2 signal differences between Clear Cell RCC and lipid-poor AML.
Topics: renal mass · frcr · genitourinary · bosniak · radiology