FRCR Part 2A · Gastrointestinal · Biliary system
Biliary System: Radiology Essentials for FRCR Part 2A
Published by FRCR AI · AI-assisted educational content
Created and overseen by Dr. Tan Min On, Radiologist — MedNex Pte. Ltd.
Published · Updated
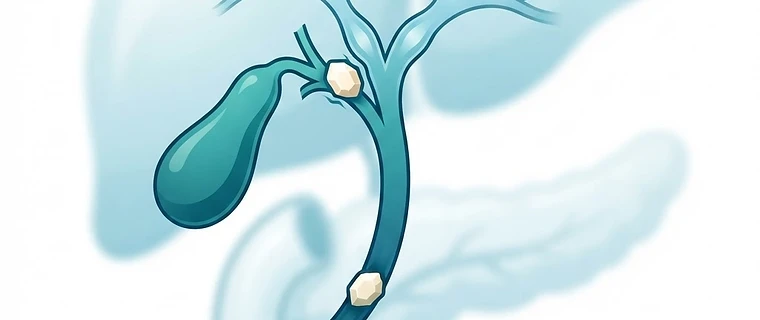
Biliary System: High-Yield Radiology Pearls
The biliary system is a core FRCR Part 2A topic, requiring a solid grasp of anatomy, pathophysiology, and the imaging hierarchy for obstruction and malignancy. Distinguishing benign from malignant biliary strictures is essential for exam success and clinical practice.
1. Anatomy and Classification of Obstruction
Intrahepatic bile ducts (left and right hepatic ducts) unite to form the common hepatic duct (CHD); the CHD then joins the cystic duct to form the common bile duct (CBD), which drains via the ampulla of Vater. Biliary obstruction is classified as intrahepatic (referred to as cholestasis) or extrahepatic, the latter being blockage anywhere along the duct system from the liver to the duodenum. Gallstones (choledocholithiasis) remain the most common cause of extrahepatic obstruction.
Exam tip: Cholesterol stones account for roughly 80% of gallstones; black pigment stones (linked to haemolytic conditions such as sickle cell disease and hereditary spherocytosis) and brown pigment stones (linked to biliary infection) each make up about 10%.
2. Imaging Hierarchy and Protocols
Ultrasound remains first-line for suspected biliary disease, reliably detecting gallstones and ductal dilation. MRCP is the preferred non-invasive technique for mapping the biliary tree and localising strictures, while EUS is favoured for tissue sampling of suspected pancreatic or ampullary malignancy.
| Modality | Clinical Use | Key Advantage |
|---|---|---|
| Ultrasound | First-line for gallstones/dilation | Non-invasive, no radiation |
| MRCP | Non-invasive duct mapping | Detailed imaging without need for endoscopy |
| ERCP | Therapeutic drainage/stone extraction | Allows stenting, sphincterotomy, and cytology |
| Pancreatic protocol CT | Staging of pancreatic malignancy | Comprehensive assessment of tumour extent |
Exam tip: NICE recommends a pancreatic protocol CT scan before biliary drainage in patients with obstructive jaundice and suspected pancreatic cancer; EUS with tissue sampling is reserved for cases where the diagnosis remains unclear.
3. Benign vs Malignant Biliary Strictures
Benign strictures include choledocholithiasis, iatrogenic injury, and primary sclerosing cholangitis (PSC) — a chronic cholestatic disorder characterised by inflammation, fibrosis, and stricturing of the intra- and/or extrahepatic ducts. Malignant strictures arise from cholangiocarcinoma, pancreatic head carcinoma (typically causing a distal CBD stricture), or ampullary carcinoma. Distinguishing between these relies on a combination of stricture pattern on cross-sectional/cholangiographic imaging and tissue diagnosis via ERCP brushing or EUS-guided sampling when the diagnosis is uncertain.
4. Mirizzi Syndrome
Mirizzi syndrome is a classic exam entity in which a gallstone impacted in the cystic duct or gallbladder neck causes extrinsic compression and obstruction of the common hepatic duct (or CBD). It can closely mimic a proximal malignant biliary stricture, making it a critical differential to exclude before planning extensive surgery.
Exam tip: An isolated CHD obstruction associated with a large stone at the gallbladder infundibulum/cystic duct should raise suspicion for Mirizzi syndrome.
5. Complications and Management of Obstruction
Acute cholangitis is a feared complication of biliary obstruction, classically presenting with Charcot's triad (right upper quadrant pain, fever, and jaundice) or, in severe cases, Reynold's pentad (the triad plus mental status change and hypotension). For unresectable biliary or pancreatic malignancy, endoscopically placed self-expanding metal stents are preferred over surgical biliary bypass for symptom relief. Emerging endoscopic bipolar radiofrequency ablation can be used before stent insertion or to clear a blocked stent, aiming to prolong stent patency and reduce symptoms.
Key Takeaway: Success in the FRCR Part 2A depends on identifying the level and cause of biliary obstruction, correlating ductal anatomy with imaging findings, and recognising the classic radiological and clinical appearances of stones, strictures, and pancreatico-biliary malignancy.
References and further reading
- Physiology, Biliary - StatPearls - NCBI Bookshelf · 2022-12-15
- Physiology, Biliary - StatPearls - NCBI Bookshelf · 2022-12-15
- Biliary Obstruction - StatPearls - NCBI Bookshelf · 2022-11-26
- Pancreatic cancer in adults: diagnosis and management - NICE · Published 07 February 2018
- Pancreatic cancer in adults: diagnosis and management - NICE · Published 07 February 2018
- Endoscopic bipolar radiofrequency ablation for malignant biliary obstruction - NICE · Published 14 November 2024
Topics: biliary · frcr · gastrointestinal · radiology · obstruction